
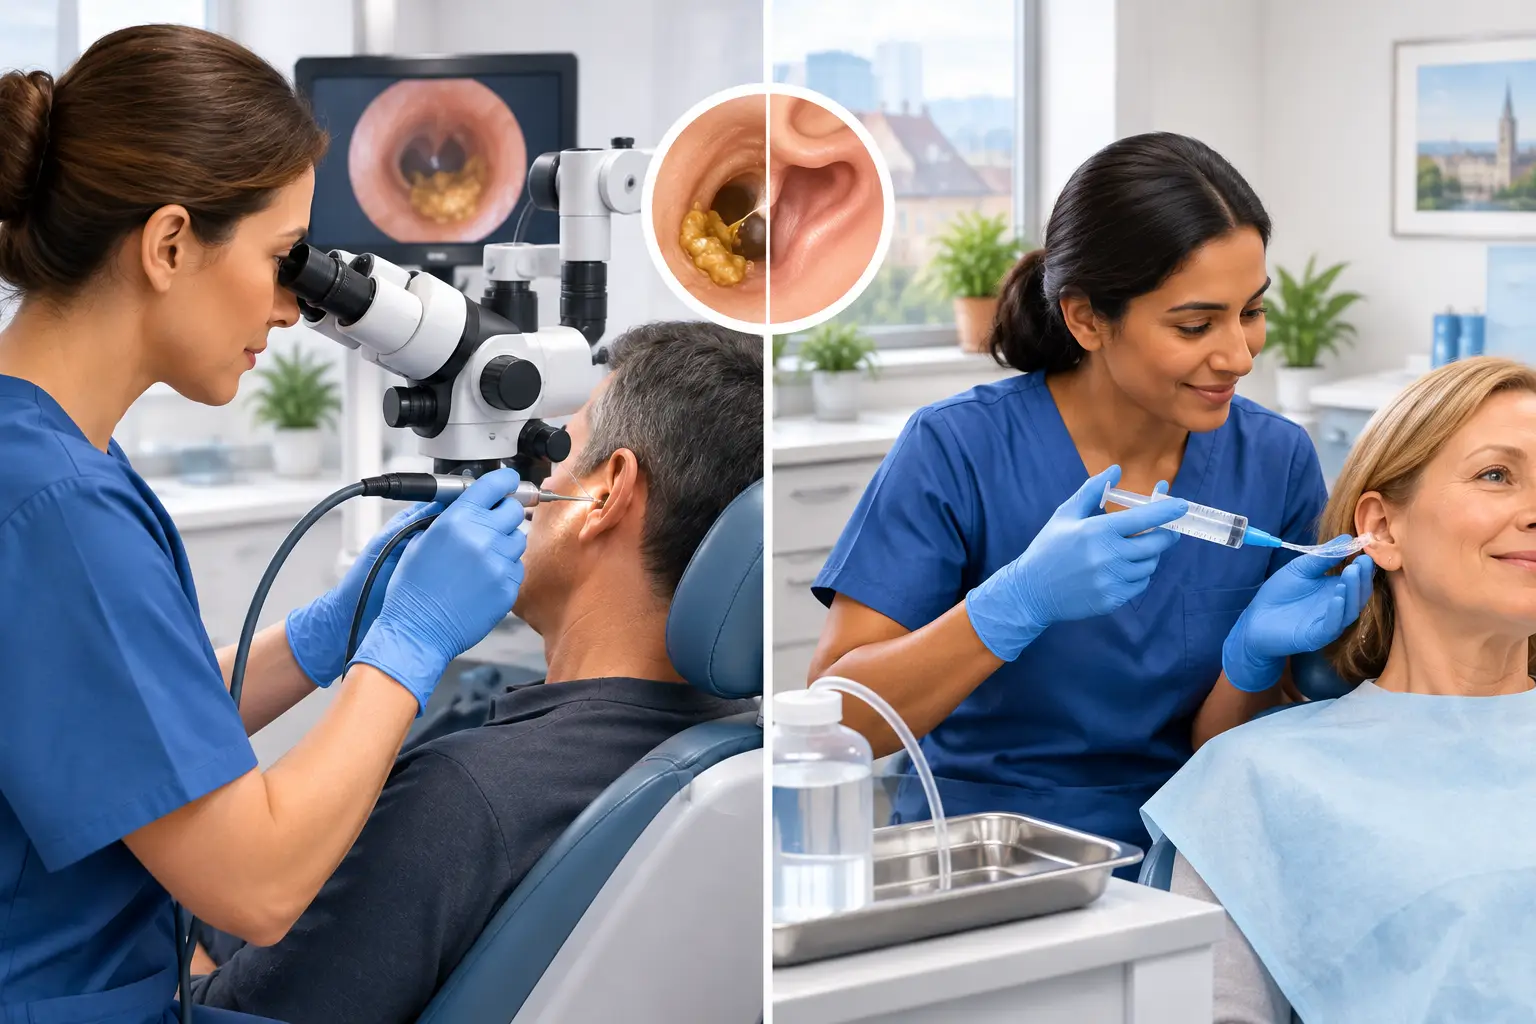
A blocked ear can make conversations sound distant, your own voice feel unusually loud and hearing aids less effective. When looking at earwax microsuction versus irrigation safety, the key question is not which method is universally best. It is which approach is suitable for your ear, your symptoms and your clinical history.
Both microsuction and irrigation are established methods of wax removal when carried out appropriately. They work in very different ways, however, and the safest choice starts with an examination of the ear canal and eardrum by a qualified clinician. Treating every blocked ear in the same way can miss the detail that makes treatment comfortable, effective and safe.
Earwax microsuction versus irrigation safety: the key difference
Microsuction removes wax using a small, low-pressure suction device under direct visual guidance. The clinician uses specialist magnification and lighting to see the ear canal as they work. Fine instruments may also be used where appropriate to gently loosen or lift wax that is dry, compacted or sitting close to the entrance of the canal.
Irrigation, sometimes called ear syringing, uses a controlled flow of body-temperature water to flush wax from the ear canal. It can be effective for wax that has been softened and is suitable to move out with water. The clinician does not remove the wax directly in the same way as with microsuction, so proper assessment beforehand is particularly relevant.
Neither approach should be chosen simply because it sounds quicker or because it worked for someone else. Earwax varies considerably. It may be soft and loose, hard and impacted, flaky, mixed with dry skin, or sitting in a narrow or sensitive canal. The condition of the eardrum and any previous ear problems also influence what is sensible.
Why microsuction is often preferred for safety
Microsuction is commonly favoured in specialist ear care because it gives the clinician a clear view throughout the procedure. Rather than introducing water into the canal, wax is removed in a controlled manner while the clinician can see the canal wall, the wax itself and, where visible, the eardrum.
This visibility matters. It allows treatment to be adjusted if wax is firmly attached, the canal is delicate, or the patient experiences discomfort. The clinician can work gradually rather than relying on water pressure to move the blockage. For people who need to return to work, travel, wear hearing aids or simply hear clearly again, that precision can be reassuring.
Microsuction may also be considered where irrigation is not appropriate, such as for someone with a history of a perforated eardrum, ear surgery, recurrent ear discharge, or grommets. A clinician still needs to assess suitability on an individual basis. Microsuction is not automatically risk-free, and it should be performed by trained professionals using suitable equipment and technique.
Some patients find the sound of suction loud or unusual. Others may notice brief sensitivity as air moves through the ear canal. These sensations are usually short-lived, but telling the clinician immediately if you feel pain, dizziness or distress allows them to pause and reassess. Good ear care is never about pushing through discomfort.
When microsuction can be more technically demanding
Very hard, dry wax can sometimes need softening before it can be removed comfortably, even with microsuction. Wax softening drops may be recommended in advance, unless a clinician has advised you not to use them. This can make the wax easier to manage and reduce the need for repeated manipulation.
There are also occasions when wax is too deep, tightly packed or close to a sensitive area to remove fully in one appointment. A careful staged approach may be preferable. That is not a failure of treatment – it is a sensible clinical decision that puts the condition of your ear first.
Where irrigation can be suitable
Irrigation can be an appropriate option for selected patients after an ear examination. It may work well when wax has been softened, the canal and eardrum appear suitable, and there is no relevant history that makes water-based removal inadvisable.
Water temperature and pressure matter. Water that is too cool or too warm can trigger temporary dizziness because the ear is closely connected to the balance system. Excessive pressure or poor technique can cause pain and may irritate the ear canal. This is why professionally delivered irrigation is very different from trying to flush an ear at home.
Irrigation also leaves moisture in the ear canal. For many people this causes no issue, but for others, particularly those prone to irritation or ear infections, avoiding retained water may be a consideration. A clinician can discuss this in the context of your own ear history rather than applying a one-size-fits-all rule.
Who should have an assessment before wax removal?
Everyone benefits from an ear examination before removal, but an assessment is particularly valuable if you have had ear surgery, a previous eardrum perforation, grommets, ongoing discharge, sudden changes in hearing, significant ear pain or repeated dizziness. These symptoms do not automatically mean wax removal cannot be carried out. They do mean the ear should be examined carefully and, where necessary, the right next step should be advised.
The same principle applies to children. Children’s ear canals are smaller, and they may find unfamiliar sounds or sensations unsettling. A patient, experienced clinician can decide whether wax is genuinely causing a problem and select a method that is appropriate for the child. Parents should avoid inserting cotton buds, hair grips or other objects into a child’s ear. These can push wax further in and damage the delicate canal.
For hearing-aid wearers, wax management is often part of maintaining clear, reliable amplification. Wax can block a hearing aid receiver or mould, affecting sound quality even when the device itself is working properly. Regular checks with a qualified audiologist can separate a wax issue from a hearing aid maintenance issue, saving frustration and helping you get the best from your devices.
Avoid home removal methods that create more risk
The urge to fix a blocked ear immediately is understandable, especially before a meeting, holiday or family occasion. Yet cotton buds commonly push wax deeper towards the eardrum rather than removing it. Ear candles should also be avoided. They do not safely remove earwax and can cause burns or leave candle residue in the canal.
Home irrigation kits may appear straightforward, but they cannot confirm whether your eardrum is intact or whether the blockage is actually wax. Using water without that information creates unnecessary risk. If you have been advised to use wax-softening drops, follow the directions given and arrange an assessment if symptoms persist or worsen.
What safe, specialist earwax care should feel like
Safe treatment is not defined by how quickly wax is removed. It is defined by proper assessment, informed consent, suitable equipment, clear communication and a clinician willing to stop or change course when your ear requires it.
At a specialist appointment, you should expect the clinician to ask about relevant ear history and current symptoms, inspect the ear, explain the recommended method and tell you what you may feel during treatment. They should also explain if wax is not the likely cause of your hearing change or if further assessment would be more appropriate.
Tragus – The Ear Specialists provides clinician-led earwax removal with microsuction as part of wider ear and hearing care. This matters because a blocked sensation is not always just about wax. An expert assessment helps ensure that you are receiving the right care for what is actually happening in your ears.
If your hearing has become muffled, your ear feels blocked or your hearing aid is not sounding as clear as usual, do not rely on guesswork or home tools. A careful examination can bring clarity first – and that is the safest place to start.